Disclaimer: This post is for informational and educational purposes only and reflects personal perspectives and cited research. It does not constitute professional medical advice, diagnosis, or treatment, and should not replace consultation with a qualified healthcare provider.See all disclaimers.
Note: This post expands on my recent ED experience which I described on social media. (You can also find it on Instagram, FaceBook, and TikTok.)
“Kindness always works.” “Just be polite.”
How many of us living with complex conditions have heard these platitudes when expressing frustration with medical providers? And how does hearing that actually make you feel when you are in acute distress?
To me, assertive self-advocacy and strategic navigation often go head-to-head with superficial ideas of “politeness.” Constantly being told to “be kind” conditions many of us—especially women—to freeze or fawn the moment an authority figure responds with skepticism. We sit on exam tables in severe pain, agonizing over whether speaking up will make us seem “difficult,” “demanding,” “rude,” or even just an “inconvenience”.
We have to unlearn that guilt. Directness is not rudeness. Stating clear facts, asking for a supervisor, or correcting a medical record is not being unkind—it is basic self-preservation. If a provider interprets calm, unwavering boundaries as “rude,” that is a reflection of their discomfort with being challenged, not a reflection of your character.
Caveat to “being respectful”
There is also a critical caveat to “being respectful”: providers must recognize that a patient who is visibly upset, tearful, angry, or exhausted is often reacting to fear, acute pain, or physical distress—not disrespecting the staff or the hospital. Take a beat, understand the overwhelming human factors at play, and see the bigger picture rather than tone-policing someone in crisis. Respect is a two-way street, but managing a provider’s comfort should never come at the expense of your life.
Strategic Navigation
When your respectful and polite attempts to communicate your needs hit a wall with a provider, strategic navigation must take over. Some examples include:
Targeted Escalation: Recognizing when a front-line provider (e.g., the Emergency Department PA/NP/Resident) is out of their depth and knowing how to request the attending physician or an on-call specialist without backing down.
Real-Time Fact Correction: Intervening when your medical history is misquoted, misunderstood, or reframed. Doing so isn’t being “difficult”, it is about your safety as a patient and can prevent misdiagnoses from following you through the system.
Breaking the “Curtain Illusion”: Calmly telling a provider you can hear them discussing your case outside the curtain, can reset the room. It transforms a dismissive sidebar into a standard of professional accountability. This becomes more important when you realize the provider is misinterpreting the concern. (e.g., “I heard you discussing my history, and I need to clarify that narrative before we move forward”.)
Provider deflection in an ER
Recognize provider deflection for what it is. When a provider says “we can’t help you here” or “call your outpatient doctor” for an emergency situation, that is rarely a reasoned medical judgment. It may be an attempt to dodge a case that they don’t understand or to clear their patient list before clocking out.
Some responses you can use in an ER when a provider says the phrases above or seems to downplay your situation, you can always say:
“I don’t feel safe leaving with [X, Y, Z]”.
“If you cannot help, then who is the on-call specialist who can”?
“If this hospital does not have [X specialist] or the tools, then I need you to arrange a formal, safe transfer to a hospital that does”.
“I understand this might be outside your comfort zone, but I need to speak with the attending ER physician or the charge nurse before any discharge paperwork is signed”.
Weaponization of passive compliance
Telling patients to simply “be kind” flattens the complex, well-documented realities of medical gaslighting—realities that disproportionately harm women, People of Color, and individuals living with complex multi-system illness. For marginalized and chronically ill patients, passive compliance is too often weaponized against them. Peer-reviewed research and major national consensus reports consistently demonstrate that:
Sex and gender bias in acute care is measurable and widespread: A 2024 analysis (Guzikevits et al, 2024) of over 21,000 emergency department visits published in PNAS found that female patients are significantly less likely to receive pain medication—both opioids and non-opioids—than male patients with identical pain scores, wait an average of 30 minutes longer for care, and are 10% less likely to even have their pain scores recorded by triage nurses. Controlled experiments confirmed that healthcare providers systematically judge female patients’ pain as less intense due to a “gender-pain exaggeration bias” that views women as overly emotional. This builds on decades of evidence showing women’s physical symptoms are routinely psychologized as emotional distress or anxiety rather than organic illness (Hoffman & Tarzian, 2001).
Acute care settings harbor documented racial disparities: In acute emergency departments, Black and minoritized patients face significantly longer wait times, lower assigned triage acuity, lower likelihood of hospital admission, and persistent under-treatment of acute pain. Even in specialized acute care like pediatric migraine management, minoritized children face significantly lower odds of receiving standard IV rescue therapies compared to non-Hispanic White children presenting with identical initial pain scores (Macias-Konstantopoulos et al., 2023; Hartford et al., 2022).
Dismissiveness directly fuels medical mistrust: A 2024 study in JAMA Health Forum examining Black patients’ experiences in the ED found that clinical dismissiveness—feeling unheard, having pain minimized, experiencing clinicians “passing them off,” and having assumptions made about their health literacy—is woven throughout emergency encounters from triage to discharge, directly confirming anticipated medical racism and driving systemic mistrust (Agarwal et al., 2024).
Twenty years of data show minimal system-level progress: The National Academies of Sciences, Engineering, and Medicine (NASEM) 2024 consensus report, Ending Unequal Treatment, confirms that despite two decades of awareness initiatives, racial and ethnic inequities in health care access, treatment quality, and clinical outcomes remain a fundamental, persistent flaw of the U.S. health care system (National Academies of Sciences, Engineering, and Medicine, 2024).
There is a profound difference between toxic compliance and assertive self-advocacy. Setting firm boundaries, correcting false medical records, and insisting that an acute physical symptom be taken seriously is not being “unkind”—it is engaging in necessary, life-preserving self-care.
What do you tell a medical provider who seems to be out of their depth or trying to rush you out the door?
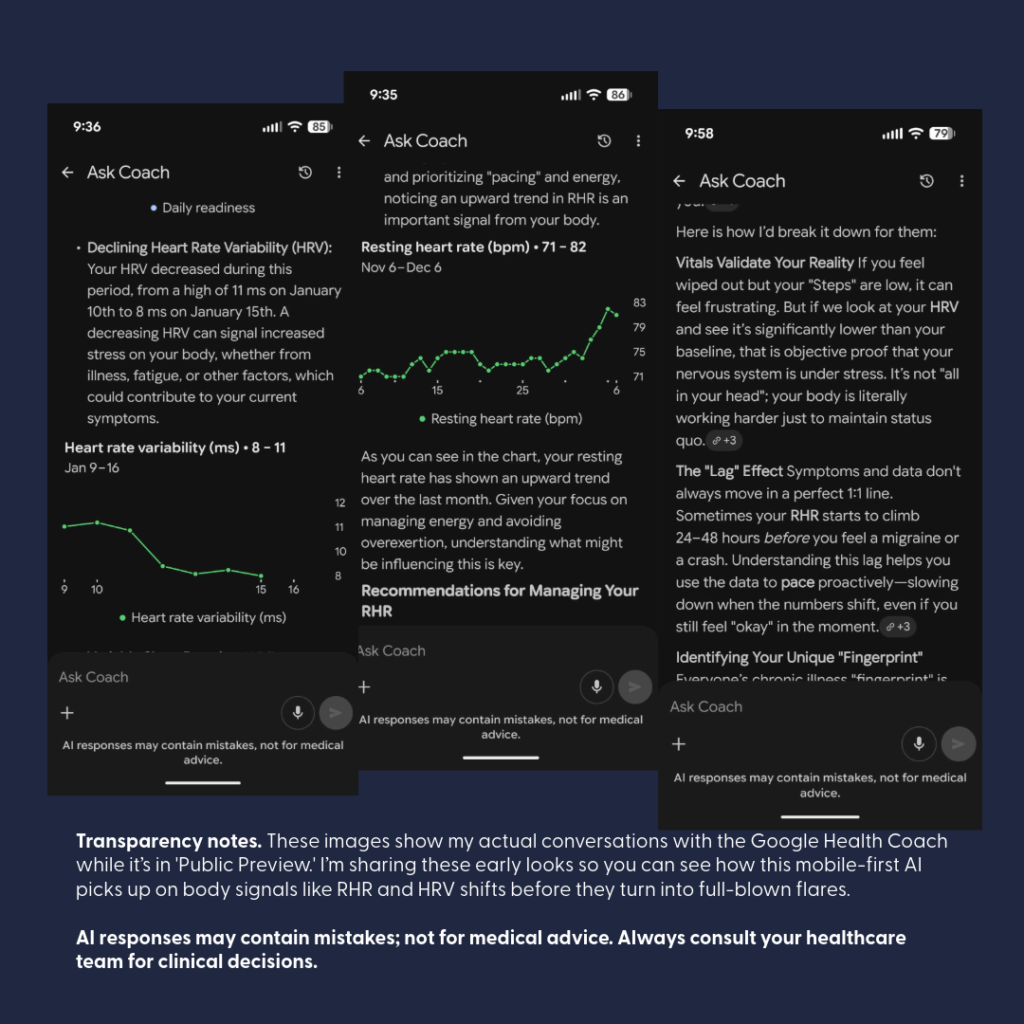
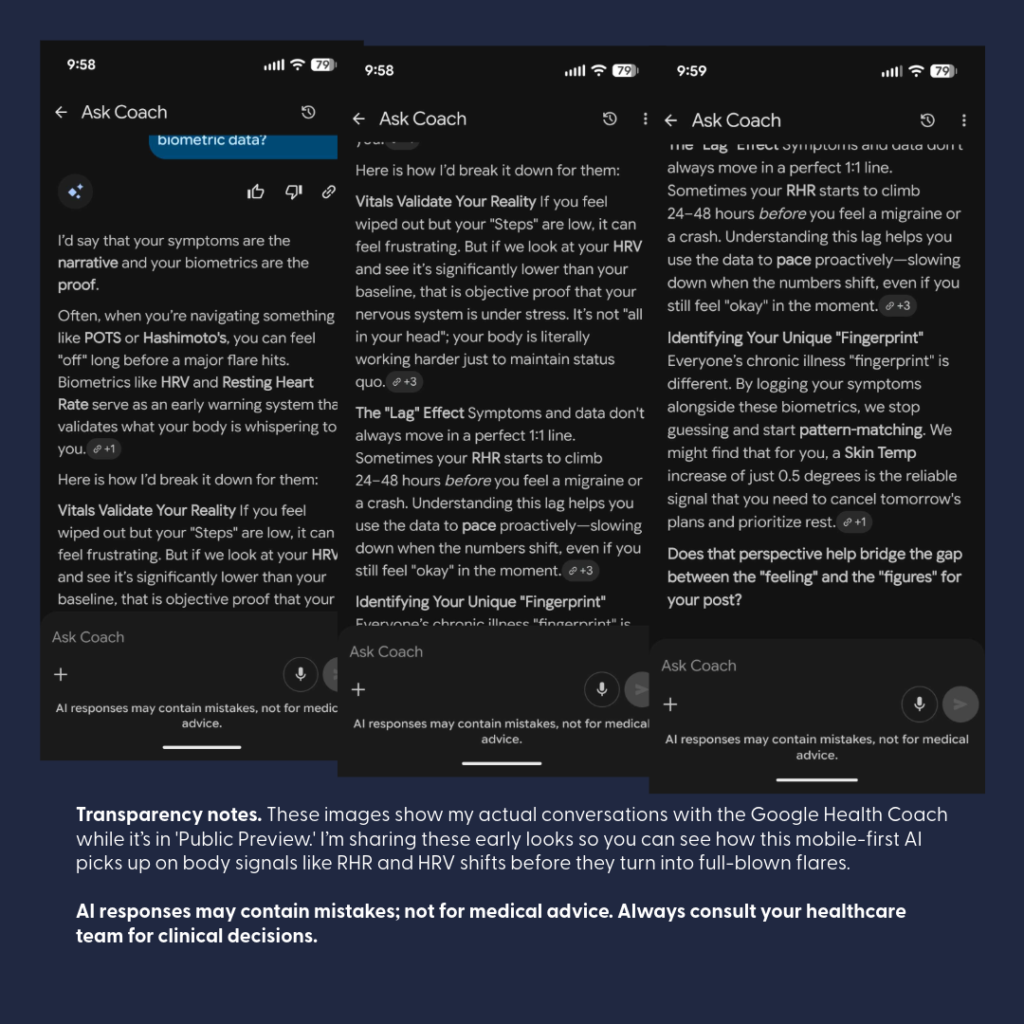
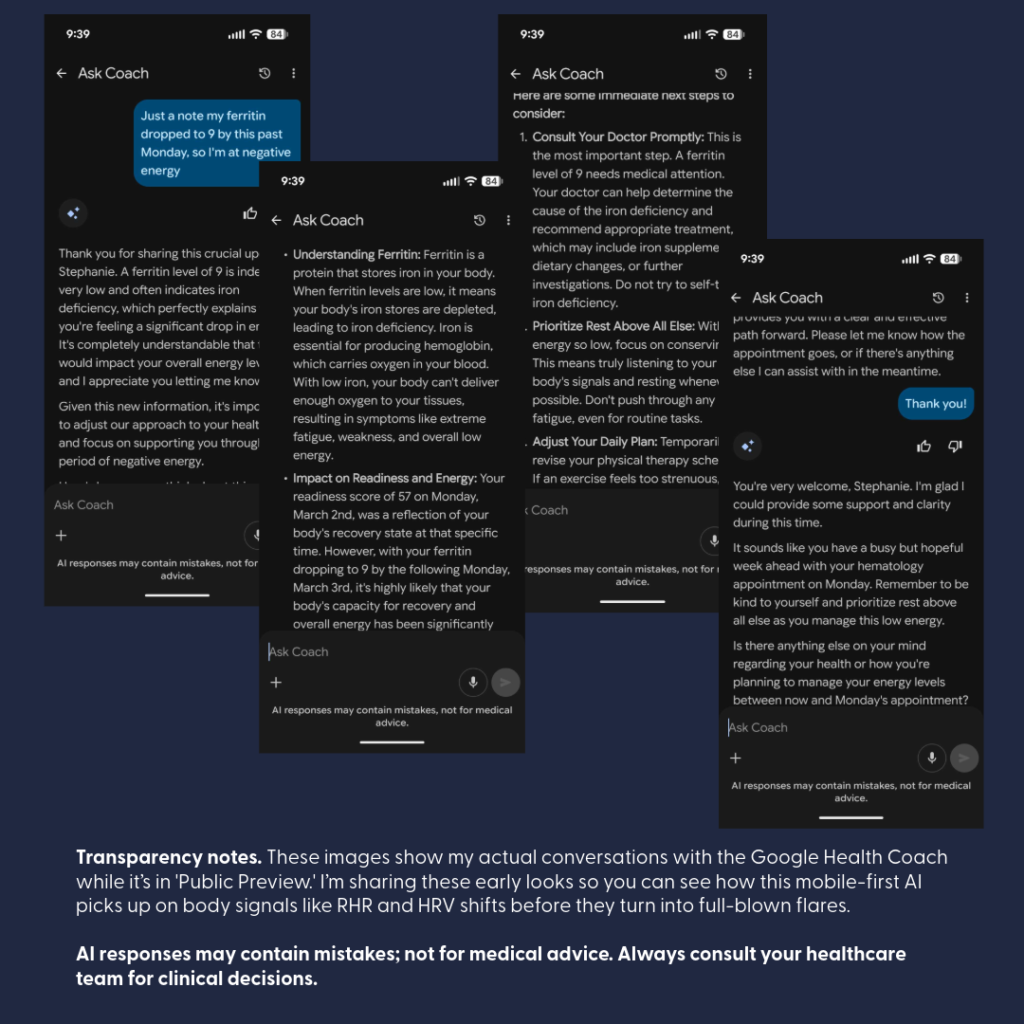
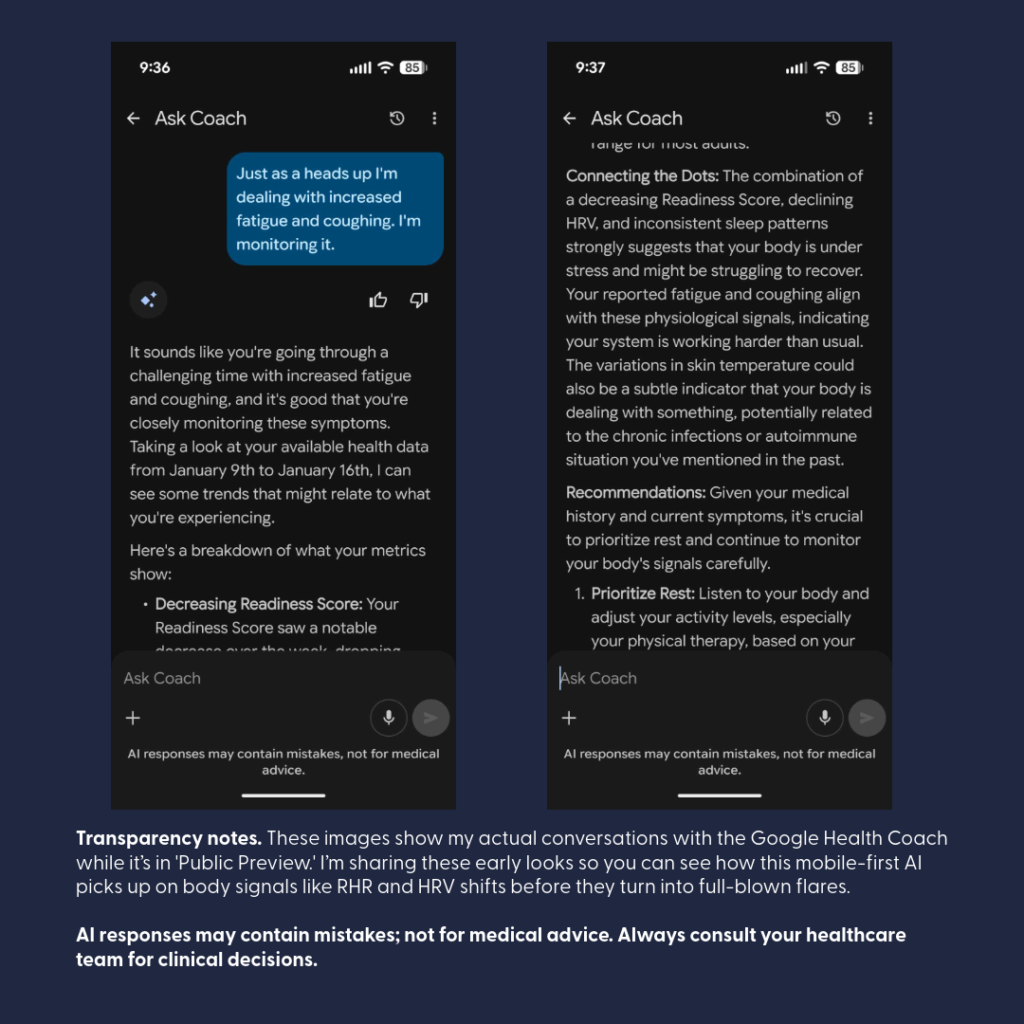
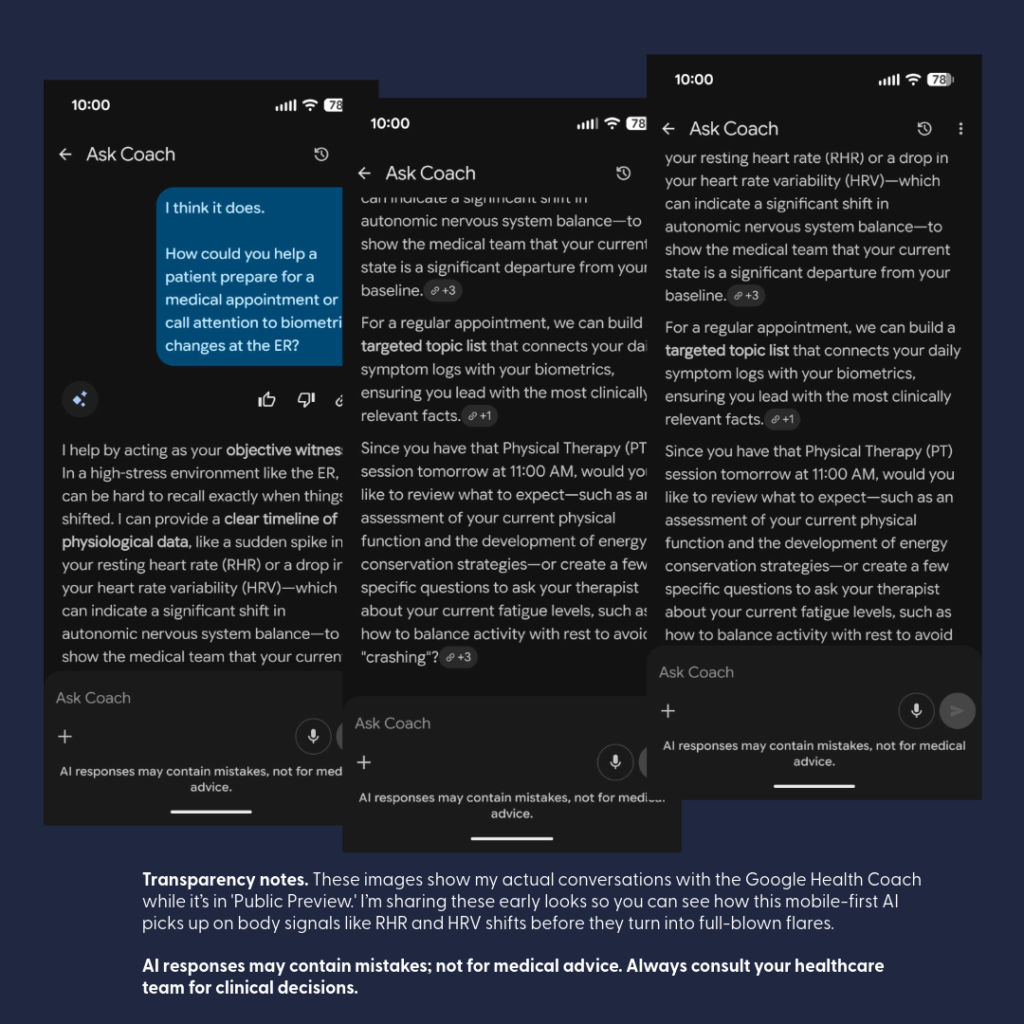
Note on Personalization: Screenshots are from my real-world testing of the Google Health (formerly Fitbit) “Coach” during its beta rollout. These represent a highly personalized conversation. Because I have been “talking” with Gemini for a long time (in Google and in FitBit Pro), the AI has a longitudinal understanding of my specific medical roadmap—including things like my C5-7 disc replacement and chronic pacing goals.
No Guarantee of Results: Each user may have a different initial experience or conversation flow. Like any “learning partner,” the depth of the insights often depends on the context you provide over time.
Beta & Evolving Features: These visuals are part of the Fitbit Labs “Public Preview”. Features like “Unusual Trends” detection are currently in testing and may change or evolve over time.
Standard Safety Reminder:AI responses may contain mistakes and are not for medical advice. Always consult your healthcare team for clinical decisions.
Let’s talk about the Google Health Rollout that began May 19, 2026! I have been participating in the beta for FitBit Pro users, and I must say, I am impressed!
(It won’t replace Guava Health for me, but it is a wonderful addition.)
Have you ever walked into a follow-up appointment, described a new and terrifying symptom, only to be told it’s “just part of the healing process” or “normal”? When a provider dismisses your symptoms, they are often guessing and comparing your body to a textbook average. To get them to move from guessing to investigating, you need objective data.
Walking into a clinic with your biometric data (including trends noted by your wearables) helps to change the dynamic: you are comparing you to YOU. Turning personal data into clinical leverage is the ultimate evolution of patient advocacy.
Google Health’s major platform rollout gives patients with chronic conditions a new set of tools to add to their baseline strategy. Here are some ways you can use this rollout to audit your care and bring the facts to your next appointment.
Master of Context and an Early Warning System
The new Google Health platform brings a clinical-grade environment directly to your phone. Google Health Premium (formerly FitBit Health Pro) serves as the home for the platform’s full Health Coach features.
Google Health is designed specifically to be the Master of Context. The mobile AI “Coach” can provide an “Early Warning System” for your day-to-day well-being:
The Coach is built to “talk” directly to you, your live wearable data, tracking key metrics like Heart Rate Variability (HRV), Resting Heart Rate (RHR), and Breathing Rate.
By continuously analyzing these metrics, the AI can pick up on subtle physiological shifts before you even consciously feel sick, helping you spot trends.
The conversational interface makes it excellent for quick, on-the-go checks to evaluate the potential impacts of medications, treatments, or even review that “something is off with my body” feeling.
Physical Health Shifts Including Infections. Often physical infection stress shows up in your “data” long before you can articulate it to a doctor. Passive wearable algorithms can catch structural emergencies early—like triggering an alert for sustained resting tachycardia (lasting over 20 minutes) or alerting patients to AFib.
The AI Coach in Google Health can take those raw metrics a step further: it can actively recognize the metrics outside YOUR normal (e.g., resting heart rate increase). Increased resting HR can be associated with autonomic imbalance (Borhani et al., 2025), illness (Michard & Saugel, 2025), and as a key metric for remote arrhythmia management (Jena et al., 2025).
In my case, “Coach” recognized something was off as shown above – and what was off – well I had a kidney stone occluding the lower pole of a ureter. (Complete duplication of my ureters bilaterally … is interesting.)Vitals Validate Your Reality. Navigating Pitfalls, Pivots, and Trajectories. During medical treatments—like managing severe iron deficiency when your Ferritin drops to a critical 9—the Coach acts as an interactive sounding board to map out symptom strategies – and to understand the labs. It also tracks your data during the intervention.
When undergoing back-to-back iron infusions, the Coach can catch delayed shifts in your biometric data indicating an “adverse reaction” to a medication (i.e., Your body and the medication – didn’t get along).
Having that data readily available allows you to make safe, immediate adjustments with your care team to swap out the problematic medication before your next round, while the Coach continues chatting through your follow-up to monitor your recovery trajectory.
Externalizing Medical Memory
When you’re dealing with chronic illness or a sudden flare, your brain is already working overtime just to handle the pain and exhaustion. Expecting yourself to remember every single detail about when a symptom started or how your heart rate shifted is like trying to run a marathon while carrying a heavy suitcase.
Using a tool like Google Health isn’t about being ‘anxious’—it’s about being smart. It’s like having a backup drive for your brain. You let the app handle the heavy lifting of storing the data so you can save your limited energy—your ‘spoons’—for actually getting through the day and focusing on your recovery.
Offloading data recall to Coach can help you save your energy for the actual clinical conversation. This can help you present objective shifts in your objective data (i.e., biometrics).
Image in part created using Gemini (Google’s AI) with some modifications by Stephanie M. Nixon.
The Gemini integration inside the Google Health Coach changes how you interact with your health metrics. Instead scrolling through a list, the Coach synthesizes complex data into clear, plain-language summaries. This can be a relief for patients who feel completely overwhelmed by the “alphabet soup” of data during a physical flare.
Conversational Symptom Logging
As a Guava Health User, I am used to a symptom-tracking checklist that leads to “insights” paired with biometric data. So switching to indirect symptom logs that came out of my conversations with the AI Coach was initially uncomfortable to me.
If you want a rigid, heavily itemized manual symptom-tracking checklist, Google Health’s baseline menus leave a bit to be desired. There is an “other” section, but it isn’t extensive, and it won’t replace the deep, structured manual entry interfaces found in heavy lifters like Guava.
But here is the magic: it completely flips the script by tracking your symptoms through fluid conversation instead. The Coach is incredibly aware of your specific, ongoing body context—for instance, it remembers and keeps tabs on a stubborn ankle injury. Instead of forcing you to click through endless checkboxes and dropdown menus when you are low on “spoons,” you simply talk to the Coach about how you are feeling, and it handles the tracking dynamically within your chat history.
Providing guidance: Reviewing symptoms when a shift is noted in the biometrics, can help tie the information together.
The Longitudinal Brain: Memory Across Threads
Traditional AI tools often suffer from “amnesia,” resetting entirely every time you open a new window. Because Google Health Coach archives core context into persistent memory logs, it builds an ongoing longitudinal understanding of your medical roadmap.
For example, if you discuss a scheduled spinal fusion that gets pushed back due to sudden low Ferritin, the Coach remembers that timeline.
Weeks later, when you open an entirely separate chat session to ask about an isolated biomarker, the AI doesn’t start from scratch—it remembers your overarching journey, bridges the gap between different conversation loops, and actively checks back in on how you’re feeling ahead of the rescheduled surgery. It behaves like a true, long-term cognitive partner rather than a temporary chatbot.
Strict Privacy Guardrails & Clinical Security
Moving your health metrics into a consumer app understandably raises questions about data security. To address this, Google has implemented rigorous technical, administrative, and physical safeguards to ensure this environment meets strict HIPAA (Health Insurance Portability and Accountability Act) standards for storing and transmitting medical records.
Here are the strict guardrails established for the Google Health app rollout:
Complete Data Separation: Your clinical and wearable health profiles are kept in strict privacy silos, entirely separated from other consumer services like your Google Search history or YouTube recommendations.
No Ad Targeting or Data Selling: Google has committed to a strict guardrail: your personal health records, diagnoses, and daily biometric data are never sold to third parties and will never be used to target Google Ads.
Legal Accountability (BAAs): Google Cloud and its health services support compliance through formal Business Associate Agreements (BAAs)—formal contracts that hold the platform legally accountable for protecting your private health information.
Total Patient Control: You retain full ownership of your profile. You choose exactly which health portals to connect, and you have the power to revoke that access at any moment.
Granular Location Protections: For privacy-conscious or neurodivergent users, GPS tracking is strictly opt-in. Location data is primarily used to track distance and pace for specific outdoor activities, and permissions can be disabled at any device or app level at any time.
De-Identified Research: Participating in health research is completely voluntary and never automatic. Before any data is utilized, it undergoes strict de-identification protocols to remove personal identifiers (like names or emails) and is aggregated with data from thousands of others to study broad public health trends.
The “Spoon-Level” Google Health Strategy
When your energy is limited, preparing for a medical visit shouldn’t waste your precious “spoons”. You can easily adapt your use of Google Health to match your capacity on the day of your appointment:
The Medium-Energy Strategy (🥄🥄): Open your mobile app and ask the Google Health Coach to generate a summary of your recent biometric shifts.
The Outcome: Print out the AI-generated summary to serve as an instant, objective “talking points” script. This ensures your most critical concerns are accurately addressed even if you hit a wall of brain fog or pain in the exam room.
Some of the ways Google Health can help with appointment prep take my app during the beta test.
The Bottom Line
Using an app to monitor your physiological baselines and symptom clusters isn’t a temporary tech trend—it is a necessary act of accessibility for patients navigating complex conditions.
You are not “obsessing” over your health; you are actively partnering in your care.
Utilizing these clinical-grade tools ensures that your medical chart reflects your true physical reality, forcing providers to move past standard labels and look directly at the facts.
Disclaimer: This post is for educational and patient advocacy purposes only. All product names, logos, and brands are property of their respective owners. “Google Health” and “Fitbit” are trademarks of their respective holders. Use of them does not imply any affiliation with, endorsement by, or sponsorship by them.
Designated Record Set: This series represents a personal, professional audit of my own legally obtained medical history and “Designated Record Set”.
Factual Basis: All clinical data points—including the 169.4-minute gastric emptying result —are pulled directly from my documented clinical records.
Advocacy Intent: My goal is to highlight systemic disparities in medical documentation and foster better clinical communication.
Non-Defamation: This audit is a critique of the content and quality of documentation and the patterns of clinical bias, rather than an attack on specific individuals or institutions.
A Note on Neurodivergent Baseline:
Contextual Accuracy: Observations regarding communication style, energy, or behavior (often labeled “manic” or “pressured” in my records) must be viewed through the lens of my documented, lifelong ADHD diagnosis.
A ‘u’ was added (AuDHD) as a late diagnosis a few years ago providing a key to understanding why so many providers saw ‘manic’ behavior where there was actually just a neurodivergent person managing a health emergency. We have to stop labeling what we don’t understand.
Have you ever read a medical note about yourself and thought: Who is this person? You are not alone. In a research study by Melanie Sloan and colleagues,¹ one patient described her medical record as:
“A deranged Twitter feed… creating a completely unrecognizable image of me as a patient and a person.”²
That quote hits hard. It describes what happens when a provider writes something subjective, negative, or dismissive in your chart. One note can change how the next provider sees you. And then the next. And then the next.
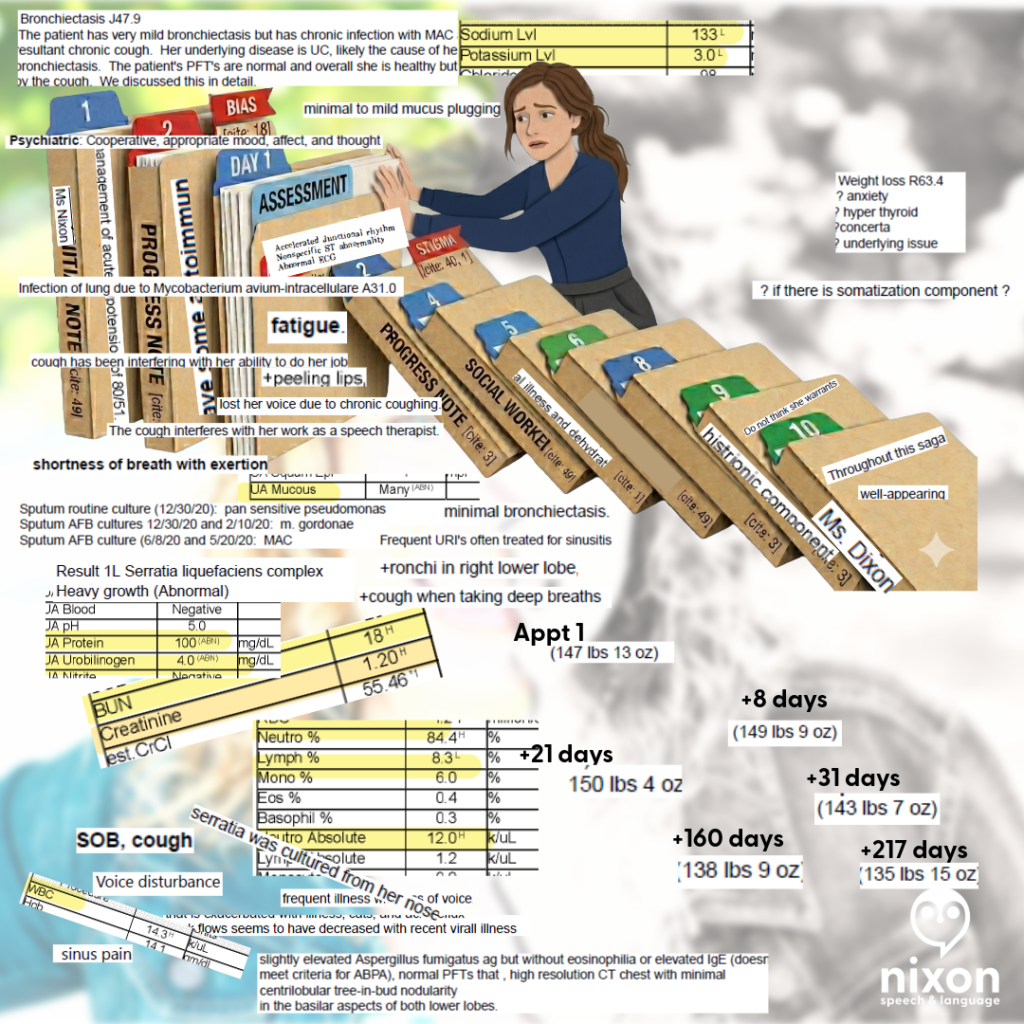
Patient safety experts call this The Domino Effect.³ This is how chart bias spreads.
What is Chart Bias?
Chart bias happens when a provider writes words that sound like a judgment of your personality rather than a description of your health. These subjective adjectives can quietly shape your care before a new doctor even walks into the room.⁴
Watch for “performance” words like:
Dramatic,Anxious, or “Histrionic”
Difficult
“Saga”, Somatic/Somatization, or “Exaggerating”
“Well-appearing” (especially when objective data says otherwise)
These words act as a path through your hospital record. They can lead the next doctor to subconsciously view your physical symptoms as a “performance,” questioning your credibility before you even speak.⁵
My Story: Same Patient, Different Stories
A few years ago, I saw my doctor for a cough that had lasted three months. I was hoarse and losing my voice. I provided a clear timeline and evidence of a bacterial infection. Instead of a diagnosis, the provider labeled my experience a “saga” and wrote that I was “demonstrating” my cough.The first note framed the encounter subjectively; the second documented objective evidence of infection.
I wasn’t “demonstrating”— when I didn’t cough, I was taking shallow breaths. Because one cough led to more coughing, and coughing led to bladder incontinence (even mild is embarrassing, iykyk).
Eight days later, a specialist looked at the same body but saw a different story:
Abnormal lung sounds (Rhonchi)
Rapid heart rate (Tachycardia)
Chest CT results: “Tree-in-bud nodularity,” which showed a likely infection.
The first note framed the encounter subjectively; the second documented objective evidence of infection.
When the Story Overwrites the Facts
Later, in the ER, a doctor labeled my coughing “histrionic” despite contemporaneous objective findings including a blood pressure of 80/51 and an elevated white blood cell count paired with elevated neutrophils (84.4%) and low lymphocytes (8.3%). I will never know if the doctor was reading the “saga” in my chart, but somehow the data on the screen didn’t receive the same emphasis in that note as his perception of me as a “chronic pain” patient.
I eventually filed a HIPAA correction to have the word “histrionic” (and other comments) struck from my record. I did this because words in a chart don’t stay in one visit. They follow you.
To this day, I still question what I could’ve done differently to avoid being misunderstood. Yes, when I go to the ER, I try to communicate past my pain past my symptoms in hopes because in my mind that is the best way to get help. Sometimes, it works … Other times, it seems providers think if you can communicate that well you can’t be “that sick”.
Why This Matters
Research shows that even one stigmatizing note can change how clinicians think about you. It can change how seriously they take your pain and how hard they look for a physical cause.3, 4, 5, 6, 7 In other words: your chart can become a story about how the provider perceives your character instead of a record of your health.¹, ²
And when I realized what that provider said and what another provider said – providers I thought I trusted, it felt like betrayal – it hurt.
Those comments didn’t match with my personality or with what I was experiencing in those moments in those hours on those days. And the thought that a provider would put those words, words I would’ve told interns not to use ever, in my chart – the chart of another provider, felt like a slap.
Could I have just ignored these comments and found new providers? Yes. But they would stay there. So I have decided to advocate with whatever spoons I have.
The “Spoon Theory” of Medical Advocacy
Dealing with chronic infections, illness, providers, employers (concerned about productivity from missed work due to the first two-three), and trying to have a balanced life – well it is absolutely fatiguing.
That means many of us come into these situations with our executive function cups full to overflowing. Such situations require working memory – we need to hold in our memory what the provider says in the current appointment at System A, what the labs say, what our imaging says, what the other provider at System B, not to mention what we might need to take care of at work or home because we may need to schedule another appointment.
So when I saw the note above in my chart, the biased note, it was like a “gut punch” that felt invalidating. It drained my energy. And I know there are other patients (many women) out there like me. I thought the ER visit that night went okay – I thought the provider understood, then I saw that note.
Yes, can I look up all the terms to understand what each lab means? But the energy – it’s overwhelming:but that costs “spoons” you don’t have.
For me, I have been using an AI Buffer – to separate the data from the disrespect, the dismissal, the gut punch, literally not being heard…
For me, these are my strategies to navigate care today at this moment. I will provide more information about these paths later – but I hope these help:
Strategy Summary
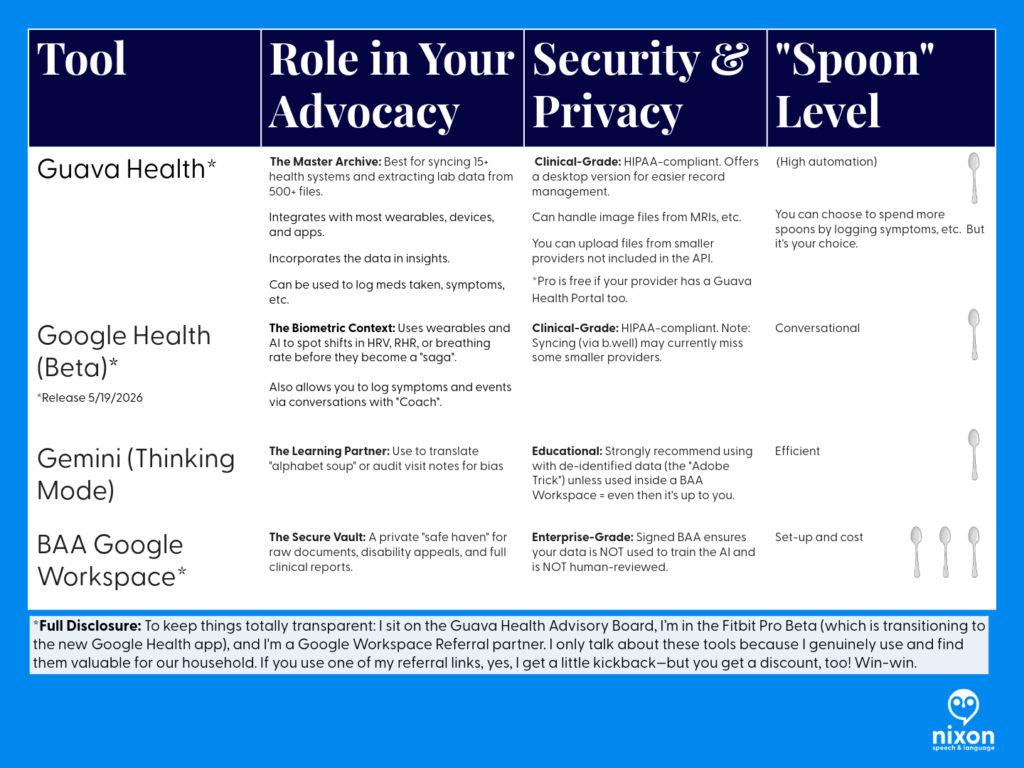
Audit for Bias: Use Gemini (Thinking Mode) to help you objectively spot if a note describes your personality instead of your physiology.
Externalize Your Memory: Use Guava’s Body Map and Medication Tracker to replace the high-stress “spotlight” of trying to remember 32 medications during a 15-minute visit.
Provide the Receipts: Use your multi-year biometric trends (Heart Rate, HRV, etc.) to prove that your symptoms are a significant shift from your baseline, not “health anxiety”.
Protect Your Privacy: If you are managing sensitive documents like disability appeals or vocational reports, move them into a Google Workspace with a BAA for maximum protection.
Why This Tech Matters
Using these tools isn’t about obsessing over every data point; it’s about Spoon Management. When you have a complex history—like Ulcerative Pancolitis or Gastrointestinal Dysmotility—you shouldn’t be expected to be your own medical librarian. These tools turn the “deranged Twitter feed” of a medical record into a searchable database that you control.
Here’s how how I go about it
1. Access Your Notes (Medical Records)
Under the Cures Act, you have the right to see your clinical notes.⁹ Don’t just read the summary; get the Progress Notes.
Tips: Sign up for the patient portal.
Use the summary like a snapshot. It’s the outline to the Progress Note (usually). But, often it just lists your current medications or the appointments to schedule, etc.
2. Create an “AI Buffer” (Protect Your Spoons)
Medical advocacy is exhausting. When a note feels like a “gut punch,” don’t waste your limited energy (“spoons”) manually looking up every term.
The Strategy: Use an AI tool to objectively “audit” the note. Ask: “Does this note focus on my health or my personality?” (If it focuses on your personality – ask yourself if that is the provider’s role in your care.)
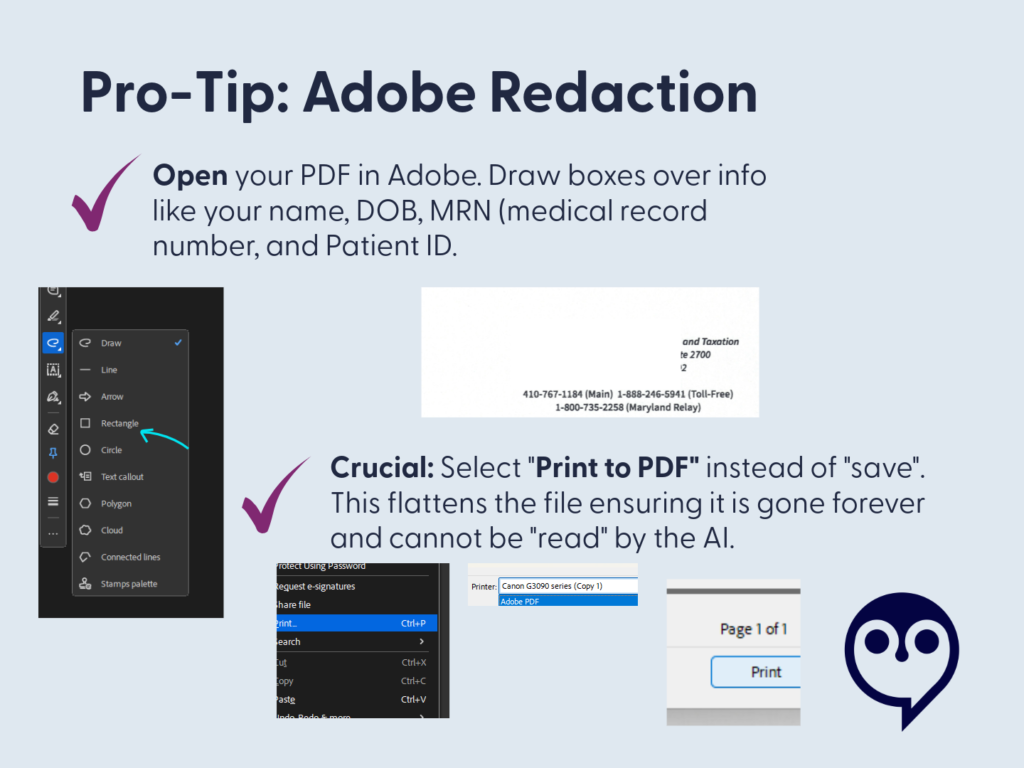
* The Privacy Choice: If you use an AI like Gemini, consider a Google Workspace with a BAA.11 This ensures your data isn’t used to train public models and isn’t reviewed by humans. It’s your “Safe Haven” for medical records. (I’ll talk more about this in another post – but I want to be sure you understand those risks.)
If you’re thinking about setting up Google Workspace for yourself, keep an eye out for my upcoming post on how I’m using it to manage our household! I’ll be sharing a deep dive, and as a member of the Google Workspace Referral Program, I’ll share some information and discount links – we will both be rewarded. <3
Accuracy Tip: Always use “Thinking” or “Pro” mode for medical analysis. “Fast” modes can miss the technical nuances you need for an appeal.12
3. Use Technology to “Translate” and “Talk”
If you struggle with dense text due to dyslexia, a stroke, or a learning disability, use these apps to hear your data:
Guava Guardian (Beta): A personal health detective. It can voice-alert you to a “split chart” (duplicate records) and helps you see how symptoms like hoarseness correlate with objective biometrics like HRV.
Google Health Coach Pro (Coming May 19): This multimodal tool allows you to talk to your data. Instead of squinting at a screen, ask the Coach to “summarize my last labs in plain English.”
4. Request a Correction
If you see something inaccurate or stigmatizing, say something.There are several paths and each depends on your comfort level with the provider.
I’ve used emails, faxes, portal messages, and phone calls to navigate these issues. In the portal, be aware that other providers in that system can likely see your messages. (I didn’t know this.)
How to start:
Contact the provider directly via the patient portal to request the correction/clarification: “I was reviewing my visit note from [Date] and noticed the history doesn’t match the objective data from my specialist. I’ve attached the relevant lab results and cultures to help clarify the timeline. Could we update the record to reflect these physical findings accurately?”
Contact the hospital’s Medical Records or Patient Advocacy department and ask about the amendment process.
For small practices, there is still a path for requesting corrections – this is your right to request it and there must be a path provided to you in that LONG HIPAA statement you received. Ask.
Phrases you can use:
“I read my note and this wording does not reflect what happened.”
“Can we focus the record on the objective lab findings from that visit?”
“I would like to add an addendum to reflect the functional impact of my symptoms.”
I’ll go into this further in a separate post. I don’t want to tell you it will always work out. But I do want you to know this is your right. And I understand it isn’t as easy as I said just now.
The Bottom Line
Your medical chart should describe your health. It should not turn one provider’s opinion into your permanent identity. If you feel like your chart describes a stranger instead of you, you are not wrong to question it.
References
Sloan, M., Naughton, F., Harwood, R., Lever, E., D’Cruz, D., Sutton, S., Walia, C., Howard, P., & Gordon, C. (2020). Is it me? The impact of patient-physician interactions on lupus patients’ psychological well-being, cognition and health-care-seeking behaviour. Rheumatology Advances in Practice, 4(2), rkaa037. https://doi.org/10.1093/rap/rkaa037
Sloan, M., Bosley, M., Gordon, C., et al. (2025). “‘I still can’t forget those words’: mixed methods study of the persisting impact on patients reporting psychosomatic and psychiatric misdiagnoses.” Rheumatology. doi: 10.1093/rheumatology/keaf115. PMID: 40037287; PMCID: PMC12107051.
Park, J., Saha, S., Chee, B., Taylor, J., & Beach, M. C. (2021). “Physician Use of Stigmatizing Language in Patient Medical Records.” JAMA Network Open, 4(7), e2117052. doi:10.1001/jamanetworkopen.2021.17052
Patient Track: Being good at makeup, didn’t mean I was well.
Disclaimers.
Professional Standards and Scope:
Credentials and expertise: Dr. Stephanie Michelle Nixon is a PhD-level Speech-Language Pathologist and consultant.
Educational purpose: The content in this series is shared for informational, educational, and advocacy purposes only.
No clinical relationship: Engagement with this content does not constitute medical advice, a clinical diagnosis, or the establishment of a patient-provider relationship.
Medical consultation: Always seek the advice of your physician or other qualified health providers with questions regarding a medical condition.
Personal Narrative & Data Integrity:
Designated Record Set: This series represents a personal, professional audit of my own legally obtained medical history and “Designated Record Set”.
Factual Basis: All clinical data points—including the 169.4-minute gastric emptying result —are pulled directly from my documented clinical records.
Advocacy Intent: My goal is to highlight systemic disparities in medical documentation and foster better clinical communication.
Non-Defamation: This audit is a critique of the content and quality of documentation and the patterns of clinical bias, rather than an attack on specific individuals or institutions.
A Note on Neurodivergent Baseline:
Contextual Accuracy: Observations regarding communication style, energy, or behavior (often labeled “manic” or “pressured” in my records) must be viewed through the lens of my documented, lifelong ADHD diagnosis.
A ‘u’ was added (AuDHD) as a late diagnosis a few years ago providing a key to understanding why so many providers saw ‘manic’ behavior where there was actually just a neurodivergent person managing a health emergency. We have to stop labeling what we don’t understand.
Which version of you is in your medical record? On the right are the labels found in my permanent charts—words like “typical,” “rushed,” “not sick appearing”, “well groomed”. On the left is the objective data my body was reporting at that exact same time.
Words have weight. After auditing my own medical charts across different institutions, it became obvious just how much weight those words carry—and how they can shadow a patient for decades. And let me say, words can hurt.
During an initial appointment years ago, a provider looked at me and said, “You look well.” My response came quickly: “I’m good at makeup.”
How many of us get up, put on our “mask” (a smile, our makeup, shallow breaths to avoid a cough), and go about our day? I know I did. I watched TikToks to improve my makeup skills while I was getting sicker. I didn’t want the world to see me looking as bad as I felt.
But do we really need to look as bad as we feel for a provider to believe the data? I once showed a provider a photo of myself before I put on my makeup that morning, just so she could see the reality of my physical state. Her response? “Why are you showing me this?”
Looking back, I realize that if a provider needs you to look “sick enough” to believe your symptoms, they aren’t the right provider for you.
Receipts
The Science: A specialist was “not convinced” I had a condition, despite a nuclear study providing a 169.4 minute gastric half-time – nearly double the normal limit.
The “Well-Appearing” Paradox: My chart once documented me as “well-appearing” and in “no acute distress” while my oxygen saturation was recorded at 65% at room air. (Note. The 65% was likely associated with PVCs.)
The “Performance” Label: My cough was described as something I “demonstrated” when I was actually navigating multiple bacterial respiratory infections (including … MAC and Staph).
The Missing “u”: My speech was labeled as “pressured,” a psychiatric term that completely ignored my AuDHD baseline (ADHD 1979 / Autism 2024; iykyk).
Audit Your Medical History
Have you ever found a statement in your records that felt more like a character critique than a clinical note?
What is one “label” a provider gave you that was the complete opposite of your reality?
How did it change the way you presented yourself at your next visit?
Provider Track: Would you want these words in your permanent record?
Disclaimers.
Professional Standards and Scope:
Credentials and expertise: Dr. Stephanie Michelle Nixon is a PhD-level Speech-Language Pathologist and consultant.
Educational purpose: The content in this series is shared for informational, educational, and advocacy purposes only.
No clinical relationship: Engagement with this content does not constitute medical advice, a clinical diagnosis, or the establishment of a patient-provider relationship.
Medical consultation: Always seek the advice of your physician or other qualified health providers with questions regarding a medical condition.
Personal Narrative & Data Integrity:
Designated Record Set: This series represents a personal, professional audit of my own legally obtained medical history and “Designated Record Set”.
Factual Basis: All clinical data points—including the 169.4-minute gastric emptying result —are pulled directly from my documented clinical records.
Advocacy Intent: My goal is to highlight systemic disparities in medical documentation and foster better clinical communication.
Non-Defamation: This audit is a critique of the content and quality of documentation and the patterns of clinical bias, rather than an attack on specific individuals or institutions.
A Note on Neurodivergent Baseline:
Contextual Accuracy: Observations regarding communication style, energy, or behavior (often labeled “manic” or “pressured” in my records) must be viewed through the lens of my documented, lifelong ADHD diagnosis.
A ‘u’ was added (AuDHD) as a late diagnosis a few years ago providing a key to understanding why so many providers saw ‘manic’ behavior where there was actually just a neurodivergent person managing a health emergency. We have to stop labeling what we don’t understand.
Clinical documentation is a record of pathology, not a character assessment. Yet, after auditing my own medical records, I found decades of “subjective” notes that had nothing to do with my physiological state and everything to do with a provider’s snap judgement and dismissal of my lived reality.
It doesn’t matter if a provider feels these words “justified” in the moment. Once they are in the patient’s chart, they become a permanent filter for every provider who follows.
The words on the black and white side minimize and dismiss both objective findings and my symptoms.
In the image above, a provider documented that my degree of disability ‘surpassed objective findings.’ In doing so, they failed to recognize my functional reality: I was a Speech-Language Pathologist unable to see my patients for 3 weeks after losing my voice to an ulceration on my vocal fold. When documentation focuses on ‘surpassing findings’ but ignores a total loss of vocational function, the clinical record is incomplete. We must document the patient’s life, not just the provider’s impression.
The Scope-of-Practice Gap:
I found repeated psychiatric judgments—labels like ‘pressured speech’ and ‘somatization’—written by specialists who were not psychiatrists or behavioral neurologists. Labeling a communication style as ‘pressured speech’ without establishing a neuro-informed baseline (AuDHD) isn’t just a misinterpretation—it is a specialist overstepping their scope to pathologize a natural speech rate instead of investigating physical health.
What they called “pressured”:
A Neurodivergent Baseline: If anyone had paused to ask, I would have laughed and told them that I had the words “SLOW DOWN!” in bold on every note for every presentation during my post-graduate education.
Physiological Distress: Rapid speech and “short rushes” are frequently associated with shortness of breath. Documentation that reaches for a psychiatric label while a patient is in respiratory distress is a failure of clinical reasoning.
Fluency Dynamics: As an SLP, I recognize these patterns as potential symptoms of cluttering among other speech and language disorders.
None of these clinical presentations require a mental health diagnosis. When we reach for mental health labels to describe a fast speech rate, we ignore the very real physical or fluency-based realities of the patient standing in front of us.
The “Incidental” Dismissal
I once had a specialist (not a gynecologist or GI) dismiss my appendectomy as “incidental” to my laparoscopy for Stage IV extra-pelvic endometriosis. When a pathology report confirms ‘Appendix – Endometriosis,’ that appendectomy is a diagnostic data point, not an ‘incidental’ event. Labeling it as such signals to every future provider that the patient’s surgical history—and their reported pain—is irrelevant.
The Receipts:
The Science: A 169.4-minute gastric half-time (normal is <90) was dismissed by a specialist who was “not convinced.”
The Paradox: A 65% O2 saturation reading was recorded alongside a note that I was “well-appearing”. (Note. The 65% O2 reading was likely associated with PVCs based on the other data in the visit.)
The Shorthand: A systemic crisis involving a 20-lb weight gain and pitting edema was labeled “long story typical for Stephanie”.
The Challenge:
The Mirror Test: If you were the patient, would you want a crisis described as “typical” for you?
Stay in Scope: If you aren’t a psychiatrist, why are you reaching for psychiatric labels to describe a patient’s communication? (Also, check with the patient. Had that provider asked me, I would’ve laughed and told her that my rate of speech has always been fast…in fact, I must actively think about it to speak more slowly.)
Watch for Bias: Literally watch for it. If you see a dismissive note from a colleague, don’t carry it forward. Check the data, ask the patient, and document the objective truth.
Let’s hold the record to a higher standard. How can we ensure our “Subjective” notes don’t do lasting harm?
In a world of sponsored “health tech” content, here is the truth:
I am a paying subscriber of Perplexity Pro ($20/mo) and a paying subscriber of the Guava Health Family Plan.
While I serve on the Guava Health Patient Advisory Panel, I do so pro bono (unpaid).
This review is not a promotion; it is a clinical audit. I’ve spent my own money on these tools because I am a “spoonie” patient, provider, and researcher searching for a way to make a complex life more manageable. (But for the record, I do accept cookies.)
The Dangerous Illusion of “All Your Data”
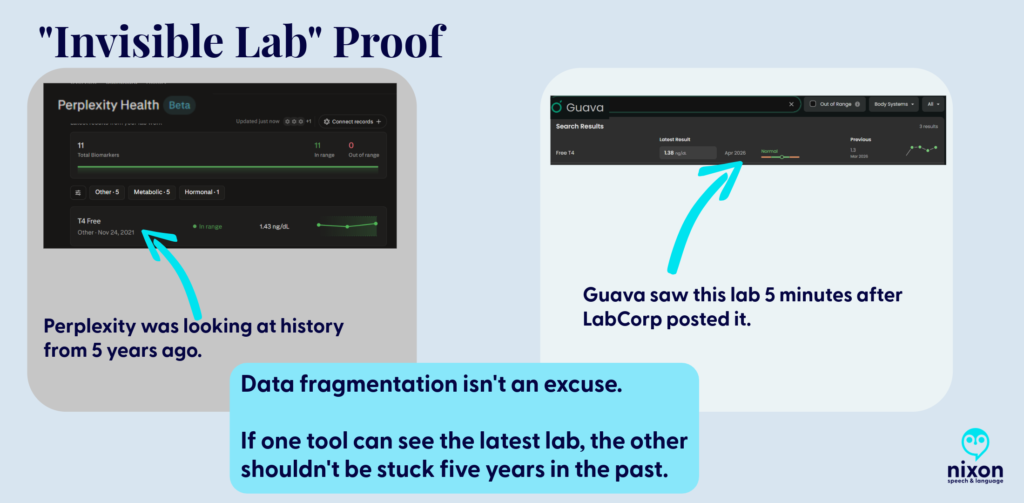
The biggest risk of Perplexity Health (Beta) is the illusion of completeness. Its marketing promises a seamless “Health Hub,” but my testing revealed a dangerous “blind spot.” Despite being connected to my EMRs, Perplexity ignored my most recent labs and defaulted to a T4 Free result from 2021 as my “current” status.
The Safety Warning: If a patient trusts Perplexity’s dashboard, they might miss key data and believe they are clinically stable when the AI is simply “ignoring” the last five years of their data because it didn’t index in a way the AI could add to your biomarkers.
The Guava Advantage: Guava understands that medical data is messy. Even when a provider doesn’t have a direct API integration, Guava allows you to upload the report. The platform doesn’t just “store” the PDF; it indexes and pulls that data into your biomarkers, ensuring your trends are accurate and complete (or as complete as the data it obtains via APIs and your uploads).
Data Latency Proof. Perplexity remained stuck in 2021 despite current data being physically present in the system.
The “Spoonie Tax”: Friction as a Barrier
Chronic illness management is often a full-time job. We use technology to save “spoons,” not spend them. Perplexity, however, added to that fatigue through technical friction:
The Quantity and Size File Wall
I could only upload 200 documents. As a person with chronic illness who has been on this earth more than say 40 years, that didn’t begin to cover even half of my documents. You might tell me, ‘Just upload the most important ones’ or ‘Import them from the provider’, well, I tried that.
The connection to my primary care provider’s office linked to her old facility vs. the current one despite having the correct address on file for her.
My dermatologist, hematologist, integrative medicine provider, endocrinologist, cardiologist, gynecologist, primary care provider, and gastroenterologist weren’t accessible via Perplexity. (And these are only a few of the providers whose data couldn’t be accessed by Perplexity.)
Note. Six of eight of the above aren’t accessible via Guava either, but I can upload those visit notes to Guava Health myself.
To only see 10% of the data can also limit seeing the big picture. So, I grouped the files using Adobe to upload them (after deleting each individual file that I had uploaded).
BUT if you’ve used AI to try to analyze data in large 150+ page files, you’ll know … it isn’t always easy. (Even Gemini tells me occasionally that my files are “too large”.)
The Administrative Demand
Then I had an interesting ‘conversation’ with Perplexity’s AI when I realized that despite syncing up with the API of one of my facilities with most of the lab data, it was missing specific data points (e.g., all Free T4 data after November 2021 despite that specific lab being drawn between 2-6 times/year.)
So I asked Perplexity Health’s AI where the labs are, and was told “You’re right that [FACILITY X] has them and that you uploaded them; the issue is that they’re not surfacing in the structured “labs/observations” stream I can see”. The AI provided several reasons for why those labs weren’t there:
They may be stored only as a scanned PDF/image of the ER report, not as discrete lab rows, so they don’t appear in the lab feed even though they’re in your chart.
The upload might be filed under “Media,” “Documents,” or an outside-records bucket that isn’t mapped into the lab/observation section my view is pulling from.
The interface that shares data from Facility X’s EMR to this aggregate view may not map ED lab panels from that date or that specific visit type correctly.
But as a patient, provider, or researcher, the issue for those of us using Perplexity Health is that those labs aren’t there, and even uploading them, doesn’t lead to them being added to the biomarker section of the site.
So when I asked Perplexity AI what I should do, it suggested that I call the hospital’s IT department to request they “re-index” my FHIR API mapping.
Fig. 2 Perplexity delegates technical labor to the patient; Guava automates the extraction through AI parsing.
Even when I provided the connections to the facilities and uploaded the records (labs and visit notes), which took A LOT OF TIME, I learned today from the Perplexity Health AI: “So even though those note sets exist in your health system, what’s flowing into this connection right now is the coded summary, not the full written note body”.
To get Perplexity Health AI to review the visit note (not the summary, the actual note), I had to reupload the visit notes to the AI side of the conversation so it could read those vs. the coded summaries.
With that in mind, Guava’s AI had me copy the line from the visit note that I wanted it to compare with my other visit notes. This is what Guava Health’s AI told me today: “I can review excerpts you paste here, but I can’t directly pull provider notes from your chart unless the app exposes them to me in this chat. If you want, paste the relevant sections”.
The Patient’s Reality
Asking a hospital’s HIM department to fix a third-party AI’s mapping is an exercise in futility. We don’t have the energy to act as unpaid data engineers for a Beta product that is already charging a premium. Also, what do you think the hospital system would say if I asked for this?
Help Desk Emails
I have emailed the help desk for Perplexity Health AI and Guava. Because I did so about the above issue with Perplexity Health AI at the suggestion of the AI after it realized it was missing significant biomarker data points, let’s address the difference.
Perplexity Health: AI Support Agent Sam emailed me back to thank me for my insights and saying that they forwarded my feedback about lab integration limitations, file upload limits, and suggestions to the product team. I sent the email April 14, 2026. I haven’t heard back.
Guava Health: This is one example of an email with the Guava Help Desk. I emailed Guava Health’s Help Desk and asked how to fix an issue when there were two sources for the same lab on August 7, 2025. On August 8, 2025, I received an email from Alex Yau, Founder and President of Guava Health to answer my question. He asked for a screenshot for an example, which I sent and he followed up with additional insight and added that he would forward it to his team to give more thought.
Note. Both Perplexity Health AI and Guava Health have discords. I am not in the Perplexity discord, but I am in the Guava Health Discord.
The Android OS Barrier
While iOS users have a native Hub, Perplexity is “desktop-primary” for Android users. Using a mobile browser to check your health data is clunky and lacks the seamless utility of a native app.
The Repository Advantage: DICOM, Quest, and GI Notes
Guava is a Source of Truth; Perplexity is a search window.
Imaging (DICOM): Guava supports actual X-ray, CT, and MRI image files. You aren’t just storing a “report”; you are carrying your entire imaging library in your pocket. (Note. You need to upload those, but, still.)
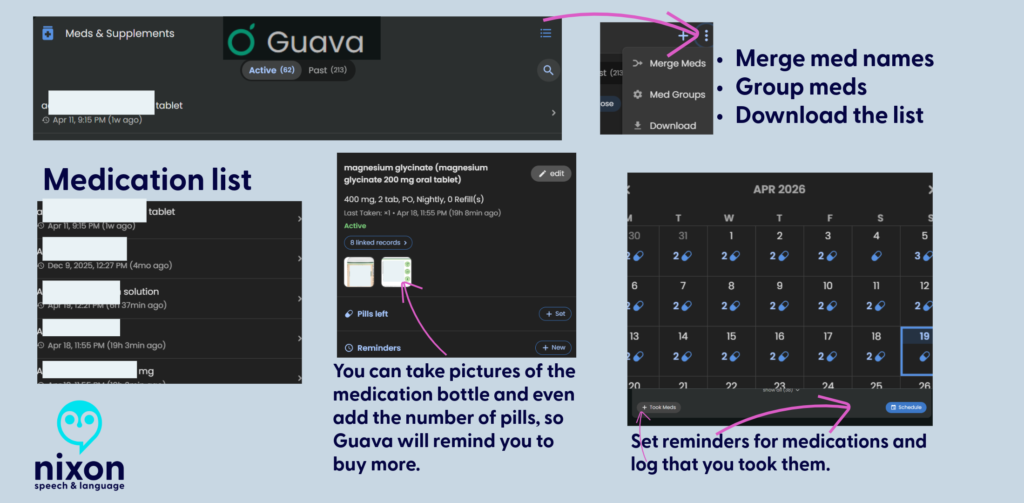
Medication Reconciliation: I manage 62 active medications. Guava allows me to merge and deduplicate them across providers. Perplexity was able to retrieve some medication lists from the facilities BUT some of those lists were outdated.
My understanding is that Perplexity Health AI integrates with Apple Health for medication management, but I use Android, so I cannot comment on that.
I can, however, comment on Guava Health’s Medication management:
Data Portability: The “Disability & Tax” Hack
The true power of a health platform is what you can do with the data.
The Guava Hack: I downloaded my encounter history from Guava and used Gemini (in thinking or data analysis mode) to generate a mileage CSV for my taxes and a total encounter count for other paperwork. Guava provided the “raw material” to simplify my legal and financial life.
Perplexity’s Failure: Because Perplexity couldn’t accurately aggregate my history, I question whether it could do so accurately.
I’ll talk more about this in another post.
Setting Health Goals in Perplexity
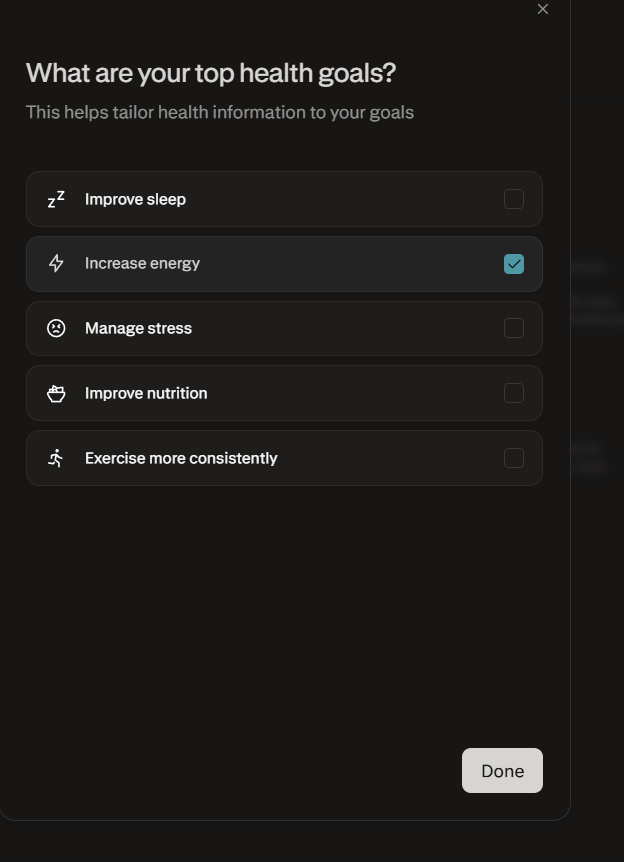
One of the most revealing disconnects in Perplexity’s “Health Hub” is the Health Goals feature, which feels fundamentally “un-Spoonie.” While the marketing suggests a personalized experience, the available goals are largely aspirational wellness targets—like “Improving sleep” or “Marathon training”—that assume a linear, healthy baseline.
For a patient managing chronic illness, these rigid targets are often inappropriate or even demoralizing, as they ignore the daily fluctuations in energy and capacity that define the “Spoonie” experience. In contrast, the Fitbit Beta with Gemini feels significantly more approachable; instead of assigning a generic wellness category, it begins with a conversation about your specific challenges and health conditions. This “Coach” approach allows the AI to adjust its insights to your actual reality, rather than forcing you into a “fitness enthusiast” mold that your body simply isn’t in today.
Taken from Perplexity Health AI. It felt like there should be an “other” option.
Auditing for Bias & The Privacy Trap
I decided to test Guava Health and Perplexity AI today on auditing visit notes for biased language from a specific former provider.
While Perplexity was helpful, I found that NotebookLM and Gemini were significantly better at finding subtle linguistic cues.
Guava Health had me copy and paste the lines from the visit note into the AI for analysis against my record, but the AI then gave me an excellent plain language overview of bias in the portion I provided it.
CRITICAL PRIVACY WARNING: Unless you have a signed BAA (Business Associate Agreement)—like Guava—BE AWARE that uploading sensitive records to any non-HIPAA compliant AI (e.g., Gemini via personal Gmail, NotebookLM attached to personal Gmail, ChatGPT, or Perplexity without the Perplexity Health piece) is only as secure as your cloud data/passwords/and more.
Final Verdict: Research vs. Management
Perplexity Health is charging a premium ($20/month) for a Beta product that requires the patient to act as a manual data entry clerk. It is for people who want to research a disease.
Guava Health is for people who have to manage one. Guava Health Premium is only $8 per month. And if your provider has a Guava Health Provider Dashboard and invites you to it, IT IS free for you. Guava Health also offers a free version to patients.
Use Perplexity if: You want a search engine for medical trends. (Maybe? But I still haven’t tested this out as much as I need to. I tend to use Google Scholar.)
Use Guava if: You need to manage medications, prepare questions for medical visits, quickly access provider notes, see overviews of your biomarkers, store your imaging, and have your data work for you in the real world.
COMING SOON:
How to get a copy of your evidence (certificate) of coverage
The Disability & Tax Guide: A step-by-step on using your medical data to navigate these two data heavy tasks.
The Provider Portal: How Guava helps your doctors help you.
Guava Tags: How I use custom tagging to find patterns in flares.
If you have questions about Guava Health, post them here!
Identification Note:Logos used for nominative fair use for critical review. Stephanie Nixon, PhD, CCC-SLP serves on the Guava Patient Advisory Panel pro bono. Review based on the April 2026 Beta of Perplexity Health.
🚨 TL;DR: The “Paddle Boarder’s Guide to Surviving the Medical System”
The Problem: For neurodivergent and chronically ill people, a change in medical plans (like a surgery delay) isn’t just an “inconvenience.” It is an enormous, destabilizing wave that threatens to knock us completely into the water.
The Metaphor: Most people navigate medical uncertainty on a stable cruise ship. They feel the waves but stay dry. We are on a stand-up paddle board. We require constant, exhaustive internal effort to balance on perfectly calm water. When the system changes, a “ripple” to the cruise ship becomes a catastrophic “tsunami” for us.
The Fatigue: We are exhausted not because we are “weak,” but because we are spending all our energy on a silent, Invisible Brace. Every admin call, sensory input, and physical pain is a wave hitting our wobbly board.
The “Flip”: When we have a meltdown, shutdown, or cancel plans, the “board has flipped.” This isn’t a failure; it’s a necessary, protective reset. We need to “sink” for a minute to stop the adrenaline of trying not to fall.
How to Help: Don’t tell us to “be flexible.” Help us stabilize. Be the solid object we can hold onto. Take over the phone calls and give us the grace to be “underwater” until the sea calms down.
How many of us have heard these words, “Be more flexible”? I didn’t realize that meant my surgery date would be doing yoga while I’m just trying to stay upright. Between the rogue waves of kidney stones and the sinking weight of low ferritin, my medical calendar has become a series of “maybe next weeks” for my lumbar fusion.
To most people, a schedule shift is an inconvenience—a slight tilt on the deck of a cruise ship. But for the neurodivergent and chronically ill, stability isn’t a given; it’s a manually operated system. We aren’t on the cruise ship. We are on a stand-up paddle board in the middle of a high-traffic wake. Each appointment that changes often means changing another appointment, changing a leave request, and navigating yet another unknown.
When the world tells us to “go with the flow,” they don’t see the Invisible Brace. They don’t see the constant, microscopic mental and physical adjustments we make just to keep our heads above the spray. In a medical system that moves like a speedboat, being “flexible” isn’t a personality trait—it’s an expensive, exhausting executive function tax that may eventually lead to our board flipping.
And sometimes, flipping the board is the only way to finally find some peace.
The First Wave
It started with a constant wave pushing my side. A kidney stone—the first rogue wave in a storm I didn’t see coming. Then came the low ferritin, the overwhelming fatigue, and the sudden, sickening realization that my carefully constructed medical plan was no longer a plan; it was a loose suggestion.
In the midst of this chaos, I kept receiving I felt like I just needed to be remain flexible.
But that is a lot to manage: Flexibility is a great trait for a gymnast, but it’s a terrifying requirement for a medical plan. Here is the reality of my recent experience:
The Paddle Board vs. The Cruise Ship
To understand why “going with the flow” is so utterly exhausting for neurodivergent and chronically ill people, you have to understand the difference in our vessels.
Most people experience medical delays or schedule shifts like they are on a massive cruise ship. The floor might tilt, the waves might get choppy, and it’s certainly annoying, but the hull is thick enough to absorb the impact. They stay dry. They stay standing.
But when you are neurodivergent—craving predictability to manage sensory and cognitive loads—or living with chronic illness, you aren’t on a cruise ship. You are on a stand-up paddle board.
Even when the water is perfectly flat, we are already expending significant executive function and physical energy just to maintain balance. Every sensory input, every social interaction, and every administrative task requires a micro-adjustment of our internal stabilization systems.
When the medical boat (the scheduling office, the specialist, the test results) suddenly changes course, it creates a massive wake. For the cruise ship, it’s just more water. For the paddle boarder, it is a catastrophic side-chop that we were not braced for. Telling ourselves to “just stand up” when we have been knocked horizontal by the wake is a misunderstanding of physics.
The Invisible Brace: Taking on Water
If it’s not the main wake from the medical boat, it’s the debris. Being neurodivergent in a medical shift (or even change in what to do next) feels like you are paddling through a constant, exhausting stream of waves you cannot anticipate.
While we are trying to keep our balance, the environment is constantly throwing more waves at us, demanding more “flexibility”:
The Rogue Wave (The Admin Avalanche): Having to make immediate phone calls to rearrange transportation, update employers, or coordinate with multiple specialists, all while processing bad news.
The Side-Chop (Sensory & Cognitive Overload): Navigating an insurance company’s phone menu or reading complex medical instructions while in physical pain and brain fog.
The Undertow (Sensory Dread): Mentally bracing for the specific sensory inputs of an impending procedure, only to have that dread extended indefinitely when the date moves.
This is Tether Fatigue. We are exhausted not because we are “difficult,” but because we have been in a permanent, tense, Invisible Brace for weeks, absorbing the kinetic energy of every ripple. Our energy reserves are fully bankrupted by the sheer volume of waves we’ve had to process just to avoid falling in.
The Grace of the Capsized Board
There comes a point where the balance is lost. The board flips. The paddle boarder goes under. To an observer, this looks like a crisis, a meltdown, or “giving up.”
But here is the secret that the neurotypical world needs to understand: Sometimes, we need to let the board flip.
When we hit the water, the Invisible Brace is finally over. We stop fighting the waves. We stop trying to anticipate the next administrative side-chop. For a moment, there is just the quiet, cold weight of the water.
We aren’t failing to cope; we are allowing the system to reboot because the cost of staying upright on a wobbly board hit by a tsunami has fully bankrupted our energy reserves. We need that “sink time” to stop the adrenaline and let our nervous systems reset before we can even think about climbing back onto the board.
How to Be an Anchor
If someone you love is neurodivergent or chronically ill and their “ship” has just flipped, don’t stand on the shore and yell at them to swim harder. Help them stabilize the water.
Reduce the “Administrative Friction”: When the plan changes, the “to-do” list explodes, requiring executive function we don’t have.
Don’t say: “Let me know if you need anything.”
Do say: “I am standing by a phone. Give me your permission, and I will handle the rescheduling calls today so you don’t have to explain your situation five more times.”
Validate the Physics, Not the Feeling: Don’t gaslight us with positivity. Acknowledge the environment.
Don’t say: “Just keep rowing! Be resilient!”
Do say: “The water is incredibly choppy right now. It makes total sense that you fell. I’m right here when you’re ready to try again.”
Grant the Grace to Sink: Let us stay underwater for a minute. We need that silence to recalibrate before we have the strength to climb back onto the wobbly board.
Examples of Stabilization in Action
Example A: Dear Medical Provider (The View from the Paddle Board)
“When you tell me a surgery is delayed or a result requires a pivot, you might see it as a minor scheduling shift. For my neurodivergent brain and my chronically ill body, it is a tsunami hitting a stationary paddle board. Please help me stay above water:
Reduce the Administrative Friction: Don’t make me the middleman between specialists. Coordinate the update with my other providers so I don’t have to spend my limited energy repeating my trauma five times.
Give Me a Fixed Point: Tell me exactly what the next step is. Ambiguity is a wave I cannot balance on.
Example B: Dear Friend (When My Board Flips)
“Right now, the floor is shaking. I am exhausted from trying to ‘stay upright’ on a board that feels every single ripple. When you see me overwhelmed, please know that I’m not being difficult—I’m bankrupt from navigating a constant stream of administrative and sensory cross-currents. Here is how to be my anchor:
Don’t Ask, Just Do: Telling me ‘I’m bringing over safe food at 6:00 PM’ is infinitely more helpful than ‘Let me know what you need.’
Let Me Sink: If I cancel, don’t take it personally. My board has flipped, and I promise I’ll climb back on when the sea calms down.”
Flexibility isn’t a personality trait; it’s an expensive resource. For the neurodivergent and chronically ill, “going with the flow” often means fighting the current just to avoid drowning. Sometimes, the best way to help us is to just let us float until the sea is still again.
Note about the art:
To capture the “layered” nature of neurodivergent life, I used a collaborative AI process to create the visuals for this post. I worked with Adobe Firefly to generate the base “paper-cut” style and used Gemini as an “Art Director” to refine the metaphors—ensuring the “administrative debris” and the “underwater reset” felt as visceral as the words themselves.
With a unique perspective shaped by my own learning disabilities, including ADHD, I bring a wealth of professional expertise in education and health policy, grant review, as well as research, evaluation, and treatment of children with speech, language, and reading disorders.
My passion lies in advocating for those who are not able to do so for themselves, leveraging my diverse background – both personally and professionally – to make a meaningful impact in the field of special education and child development.
Stop scribbling on scrap paper. Here is the exact system I use to hold insurance companies accountable (and keep track of what has been said).
In my last post, I talked about the importance of documenting every single interaction with your insurance company. But let’s be honest: when you are managing a chronic illness, working, or just living life, finding a notebook and a working pen while on hold is just one more hurdle.
My husband and I realized early on that we needed a system that was fast, shared, and impossible to lose.
Our solution? A simple Google Form.
It lives as an icon on our phone home screens. When we get on a call, we tap it, fill in the blanks while we talk, and hit submit. It automatically saves everything into a spreadsheet that we can search later.
Why This Works Better Than a Notebook
It Prompts You: You never forget to ask “Who am I speaking with?” because the form requires you to type it in.
It’s Collaborative: If my husband takes a call, I can see the notes instantly on my computer. No more “Did you call them?” arguments.
It Creates a Timeline: When you need to file a grievance (like I did), you just open the spreadsheet and copy-paste the entire history.
The Fields You Need (Steal My Form)
I created a free Google Form with these specific questions. You can copy this exact structure:
Patient calling about: (Checkbox: … Names of those in the household, etc.)
Date called: (Date picker)
Who contacted? (Checkboxes: Benefits, Care Management, CVS Caremark, HR, etc.)
Method of contact: (Checkboxes: Phone, Email, Secure Message)
Did I record the call? (Yes/No – Check your local lawsas many areas require you to ask permission to record.)
My Script: “I need to record this call so I have a record of what to do next. Do I have your permission to record?” Note. Be sure to note this to any new call participants.
Note: If they say “No,” I immediately ask: “Since you are recording this for quality assurance, can I request a copy of that recording for my records?” (This usually changes the tone of the conversation!)
Name of representative: (Crucial! Always ask for this first)
Reason for call: (e.g., Prior Authorization, Billing Error, Benefits Question)
Summary of call: (What did they say? What did you say?)
How long were you on the call? (This is important evidence for complaints)
Action items: (What did the representative promise to do? What do you need to do?)
Follow-up date: (When should you check back?)
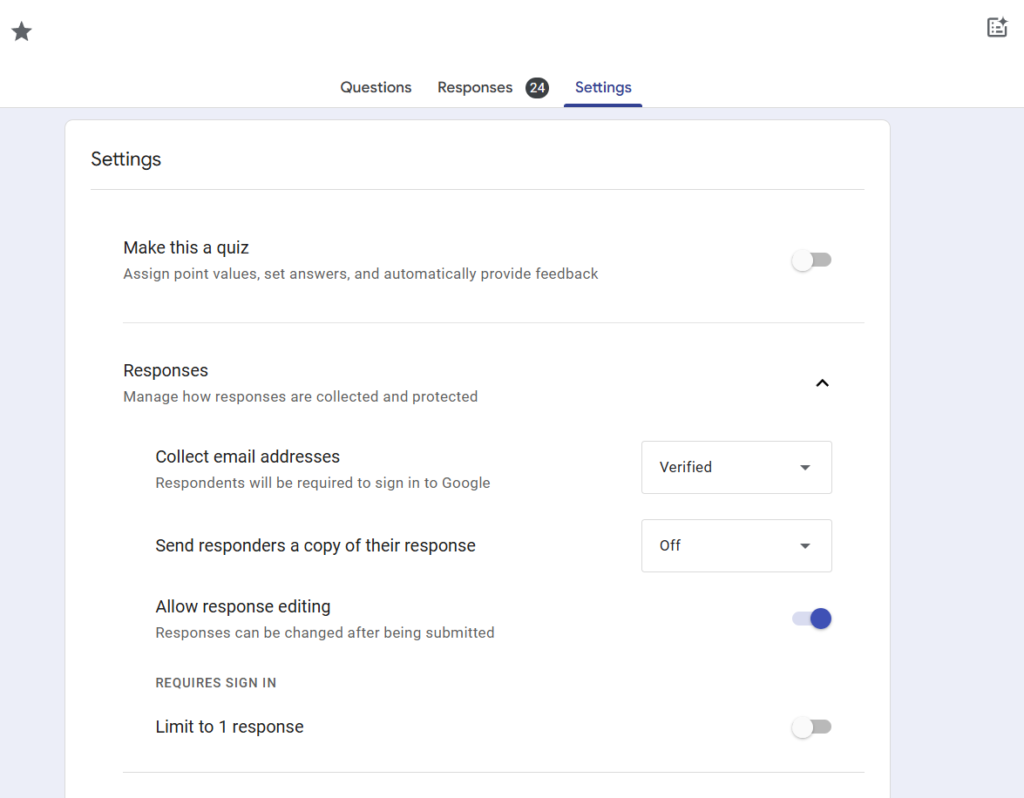
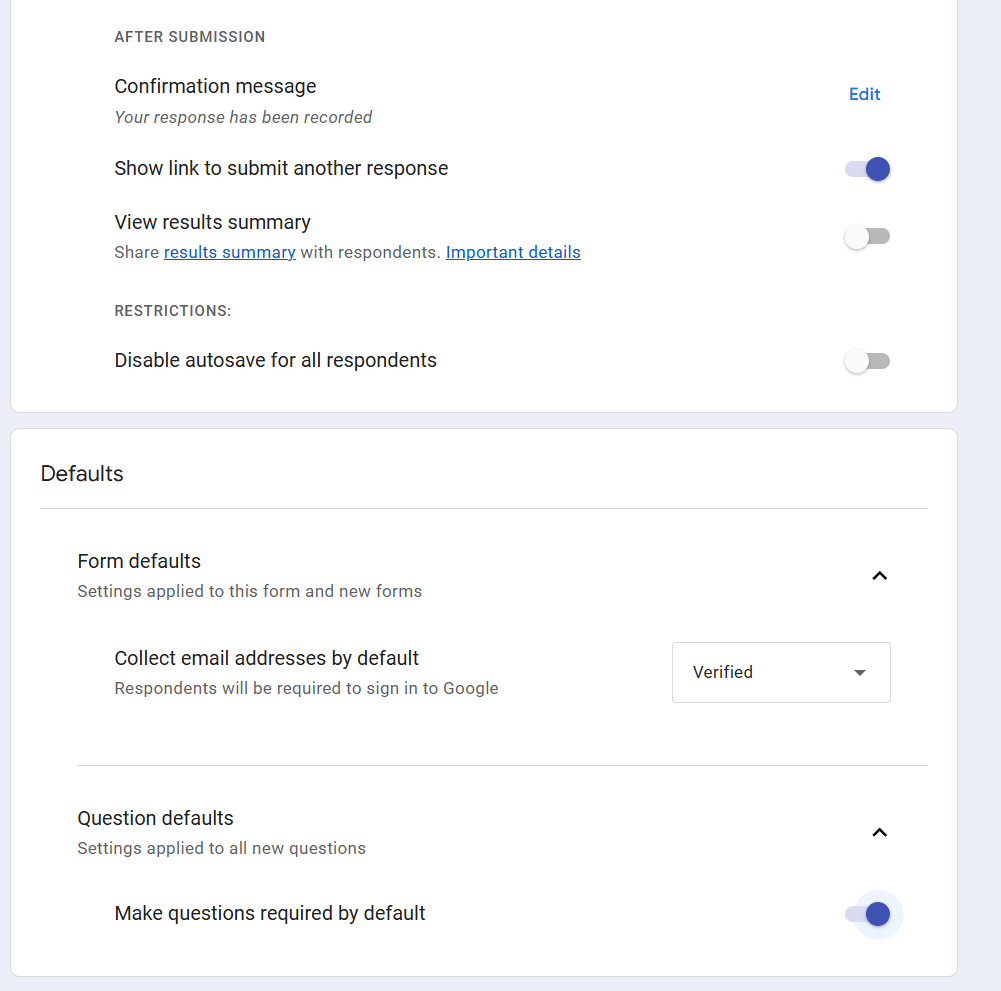
Header for your form.Settings for the form. Some are personal, but this let’s me and Josh know who entered the data.I have the email addresses required by default and the same for questions. (You can set some as not required.)
How to Set It Up
Go to forms.google.com and click “Blank Form.”
Add the questions listed above.
Click “Send,” copy the link, and email it to yourself and your spouse/caregiver.
Pro Tip: Open the link on your phone, tap “Share” (iOS) or the menu dots (Android), and select “Add to Home Screen.” Now it looks and acts just like an app.
The Result
When my pharmacy billing nightmare happened, I didn’t have to rely on my foggy memory. I opened my spreadsheet and saw exactly who disconnected on me on January 29th, and exactly what “Curtis” told me on February 6th.
That data wasn’t just notes; it was evidence. And evidence is the only thing that wins insurance appeals.
Disclaimer: I am a Speech-Language Pathologist and person with chronic illness, not an insurance broker or attorney. This post shares my personal experience and is not intended as legal or financial advice.

















Leave a Reply